
A modern advance for large, giant, and wide-necked brain aneurysms that are difficult to treat with coiling alone.
Flow diverter stents are biocompatible, finely woven metallic mesh tubes placed inside a brain blood vessel to divert blood flow away from an aneurysm. Rather than being packed inside the aneurysm like coils, the flow diverter sits in the parent vessel across the neck of the aneurysm — redirecting blood along the normal vessel while reducing flow into the aneurysm, and preserving flow to healthy side branches.
Each device is made of tightly braided wires — usually between 48 and 64 of them — which increase the metal density across the vessel surface to achieve this diversion effect.
Unruptured saccular aneurysms with neck >4mm, or neck-to-dome ratio below 0.5.
Fusiform, dissecting, and blister aneurysms, irrespective of size.
Ruptured aneurysms that are not suitable for coiling or clipping.
Around 6 types are currently available. Pipeline and Surpass are FDA-approved.
The procedure is minimally invasive, performed under general anaesthesia and usually lasting 2 to 3 hours. Access is through a small nick in the artery at the groin (femoral route) or wrist (radial route) — no sutures or long cuts are needed. Thin catheters are navigated up to the brain vessels, and the flow diverter is delivered and deployed across the aneurysm.
Antiplatelet (blood-thinning) medication is started at least 6 hours before the procedure and continued for at least 1 year afterwards. Follow-up angiography (CT or DSA) is done at 3, 6, and 12 months to confirm the aneurysm has fully closed.
In experienced hands, risks are minimised through careful planning and device selection.
Only a small nick in the groin or wrist — no open incision.
Fast recovery compared to open surgical approaches.
Imaging at 3, 6, and 12 months confirms complete aneurysm closure.
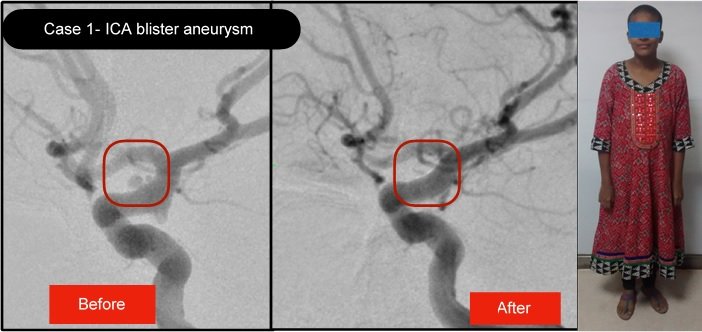
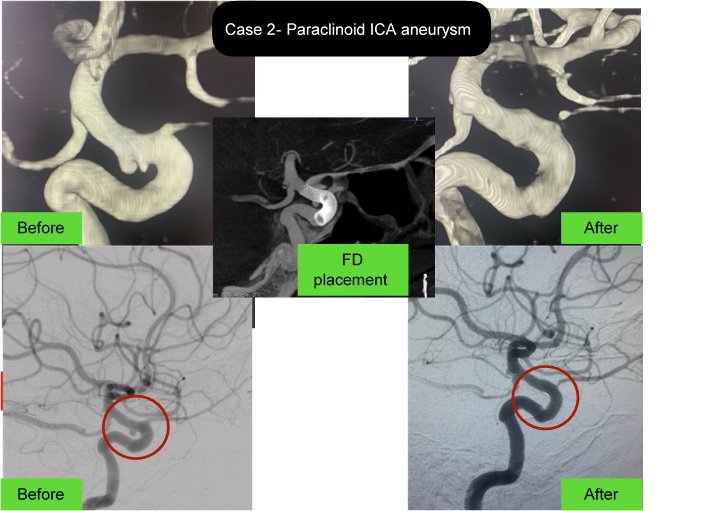
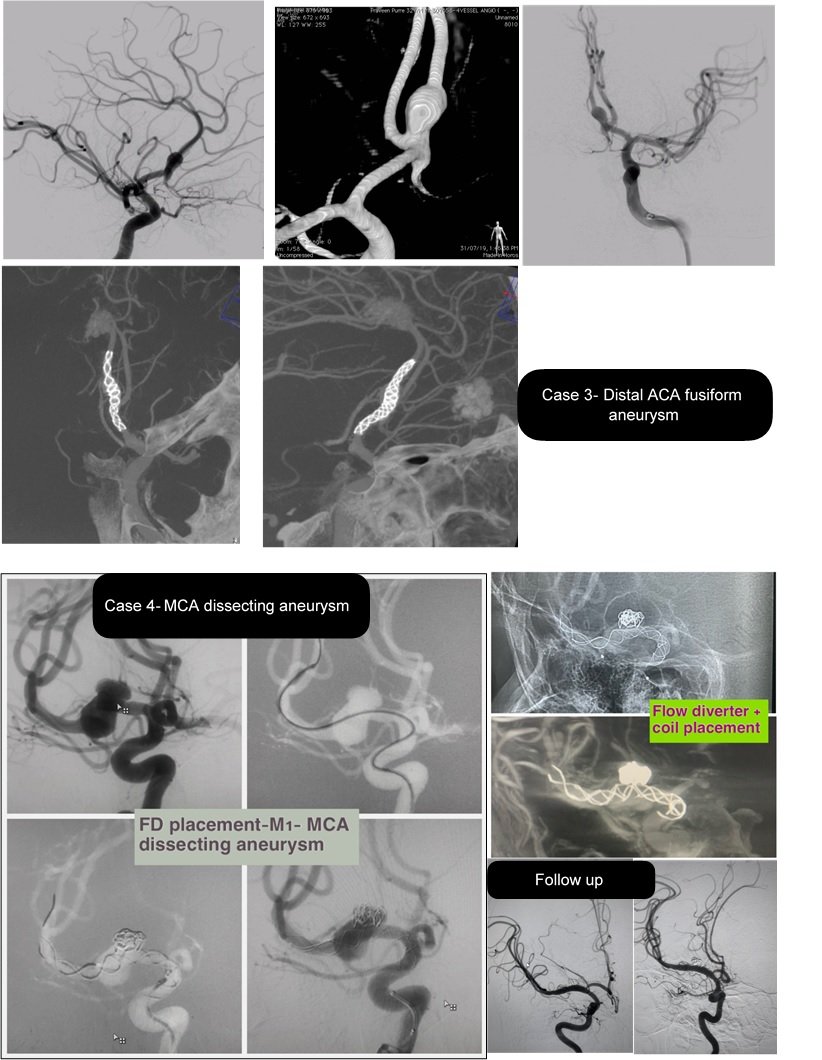
A flow diverter stent is a fine, woven metallic mesh tube placed inside a brain blood vessel to divert blood flow away from an aneurysm. It sits in the normal vessel across the aneurysm neck, causing the aneurysm to gradually shrink and close off over 3 months to 1 year, while preserving normal blood supply.
Flow diverters are used mainly for aneurysms that are hard to treat by coiling or clipping — including wide-necked aneurysms (neck over 4mm), and fusiform, dissecting, or blister aneurysms of any size. They are also used for some ruptured aneurysms not suitable for coiling.
Instead of being packed inside the aneurysm, the flow diverter redirects blood along the normal vessel and reduces flow into the aneurysm. Over 3 to 12 months the aneurysm clots off and shrinks, while healthy side branches keep their blood supply.
Around six are available: Pipeline (Medtronic), Surpass (Stryker), Silk Vista (BALT), FRED (MicroVention), Derivo (Acandis), and p64/p48 (Phenox). Pipeline and Surpass are FDA-approved. The specialist selects the device based on the aneurysm and vessel anatomy.
The procedure is done under general anaesthesia and takes about 2 to 3 hours. Hospital admission is usually 2 to 3 days. Because there are no cuts or sutures, most patients can walk the next day.
Yes. Antiplatelet (blood-thinning) medication is started at least 6 hours before the procedure and continued for at least 1 year afterwards. Follow-up angiography at 3, 6, and 12 months confirms the aneurysm has closed and guides adjustment of the medication.
In experienced hands the complication rate is under 5%. Possible issues include a blood collection at the groin puncture site and, less commonly, minor or major stroke. Careful planning, device selection, and post-procedure care minimise these risks.
Yes. Large, giant, and complex aneurysms are exactly what flow diverters are designed for. They have significantly improved the safe, durable treatment of aneurysms that were previously very difficult to manage with coiling or surgery.
At Neuro & Vascular, flow diverter placement is performed by Dr. Suresh Giragani, Consultant Interventional Radiologist, Hyderabad, with over 18 years of experience in neurovascular intervention including coiling, stent-assisted coiling, and flow diverter placement.
Book a consultation with Dr. Giragani, or send your scans and reports for a specialist second opinion.