
Minimally invasive endovascular treatment for brain aneurysms — coiling, stent-assisted coiling, and flow diverter placement — performed by Dr. Suresh Giragani.
A cerebral aneurysm is a balloon-like swelling of a brain blood vessel. Their incidence is about 1 in 1,000 in the general population, and they are more common in women. The exact cause is not fully understood, but they are associated with certain genetic conditions, including autosomal dominant polycystic kidney disease and Ehlers-Danlos syndrome. High blood pressure (hypertension) is known to accelerate the growth of aneurysms.
Many unruptured aneurysms cause no symptoms at all and are found incidentally during scans done for other reasons. A ruptured aneurysm typically causes a sudden, severe "thunderclap" headache, along with neck stiffness, nausea, vomiting, sensitivity to light, or loss of consciousness — this is a medical emergency.
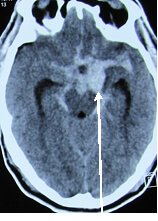
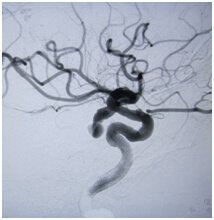
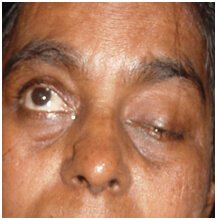
Not all aneurysms require treatment, but certain ones always should.
All ruptured aneurysms should be treated as early as possible to prevent re-rupture — this is an emergency.
Aneurysms causing symptoms from compression on nearby structures should also be treated.
Treatment is generally advised for unruptured aneurysms larger than 5mm in an intradural location.
The decision is made individually based on age, family history, and personal history.
According to American Stroke Association guidelines, when an aneurysm is suitable for both approaches, endovascular coiling is generally preferred over surgical clipping. The right choice depends on the aneurysm's location and shape.
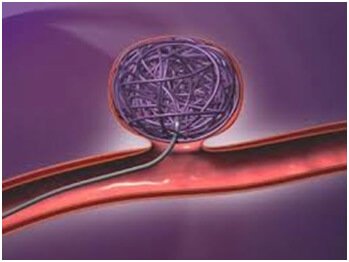
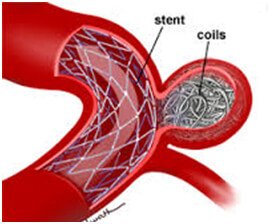
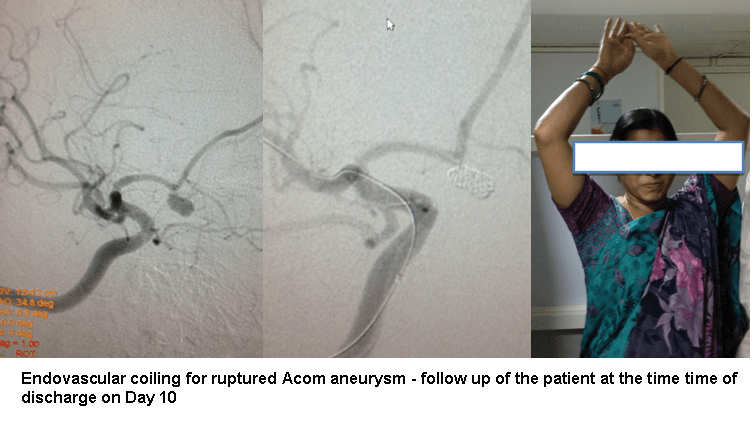
Endovascular coiling is a minimally invasive procedure that seals a brain aneurysm from the inside using soft, malleable platinum coils. Through a pinhole in the thigh, a fine catheter is guided up to the aneurysm, and coils are carefully packed inside the aneurysm sac to block blood flow into it, while preserving the normal brain vessel. Depending on the aneurysm's anatomy, different techniques may be used, including balloon-assisted coiling and stent-assisted coiling.
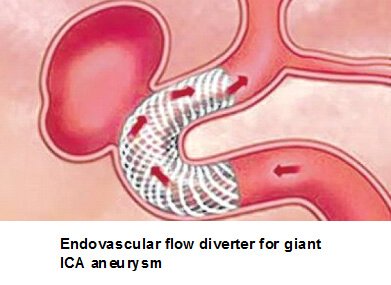
Flow diverter stents are advanced devices used to treat large, giant, or complex aneurysms that are difficult to treat with coiling alone. A flow diverter is a fine mesh tube placed across the neck of the aneurysm inside the parent vessel; it redirects blood flow along the normal vessel and away from the aneurysm, causing the aneurysm to clot off and shrink over time. Newer intrasaccular devices (such as WEB and Contour devices) sit inside the aneurysm sac and are used for certain wide-necked aneurysms. These advances have significantly reduced the recurrence of large and giant aneurysms.
Short for unruptured aneurysms; longer for ruptured ones, as complications like vasospasm need time to settle.
Regrowth after coiling is uncommon, especially for small aneurysms. Stent-assisted coiling & flow diverters reduce this further.
The chance of a regrown aneurysm rupturing after coiling is only about 1.2%. Follow-up MR angiography is advised.
Precise device selection and placement lowers complication risk — choose a high-volume neurointervention specialist.
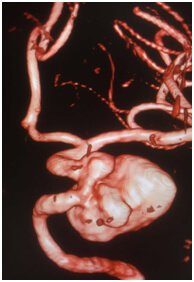
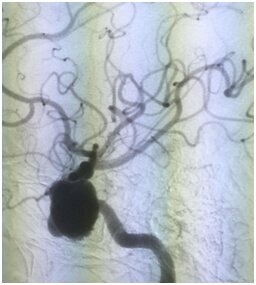
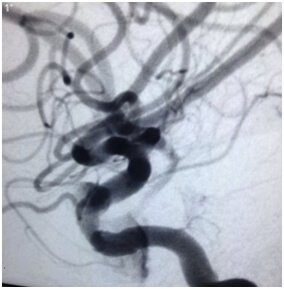
A brain (cerebral) aneurysm is a balloon-like swelling in the wall of a blood vessel in the brain. It affects roughly 1 in 1,000 people and is more common in women. The main danger is rupture, which causes bleeding in the brain (subarachnoid haemorrhage).
No. All ruptured aneurysms need urgent treatment to prevent re-rupture, and aneurysms causing pressure symptoms should be treated. For unruptured aneurysms found incidentally, treatment is generally advised for those larger than 5mm in an intradural location, decided case by case based on age, family history, and personal factors.
Both are effective. According to American Stroke Association guidelines, when an aneurysm can be treated by either method, endovascular coiling is generally preferred over surgical clipping. Coiling is minimally invasive, performed through a pinhole in the thigh without opening the skull, allowing faster recovery. The right choice depends on the aneurysm's location and shape.
Coiling is a minimally invasive procedure that seals the aneurysm from inside using soft platinum coils, delivered through a catheter from a pinhole in the thigh. It blocks blood flow into the aneurysm while preserving the normal vessel. Balloon-assisted and stent-assisted variations are used depending on the aneurysm's anatomy.
A flow diverter is a fine mesh tube placed across the neck of an aneurysm to redirect blood flow along the normal vessel, causing the aneurysm to clot off and shrink over time. It is used mainly for large, giant, or complex aneurysms that are hard to treat with coiling alone.
For an unruptured aneurysm, the stay is usually short. For a ruptured aneurysm, it is longer, because complications such as vasospasm and electrolyte changes need time to settle. Treating an aneurysm before rupture is generally less risky.
Regrowth is uncommon, especially for small aneurysms. Large and giant aneurysms have a slightly higher chance, though stent-assisted coiling and flow diverters have reduced this considerably. The chance of a regrown aneurysm rupturing after coiling is only about 1.2%. Follow-up with MR angiography is advised.
Coiling is a well-established, minimally invasive procedure. Outcomes depend strongly on the experience of the interventional radiologist, particularly for ruptured or complex aneurysms. In expert hands, it carries a lower risk than open surgery for suitable aneurysms.
At Neuro & Vascular, brain aneurysms are treated by Dr. Suresh Giragani, Consultant Interventional Radiologist at Apollo Hospitals, Jubilee Hills, Hyderabad, with over 18 years of experience in neurovascular intervention including coiling, stent-assisted coiling, and flow diverter placement.
Book a consultation with Dr. Giragani, or send your scans and reports for a specialist second opinion.