
Minimally invasive treatment for inoperable liver tumors — RFA, microwave ablation, TACE and TARE — without open surgery.
Cancer treatments by an interventional radiologist fall into three groups: curative treatments (RFA, microwave ablation, ethanol injection), disease-modifying treatments (TACE, TARE), and supportive/symptomatic treatments (biliary drainage, portal vein embolization).
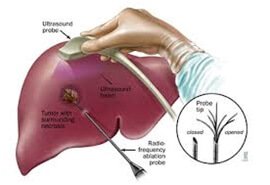
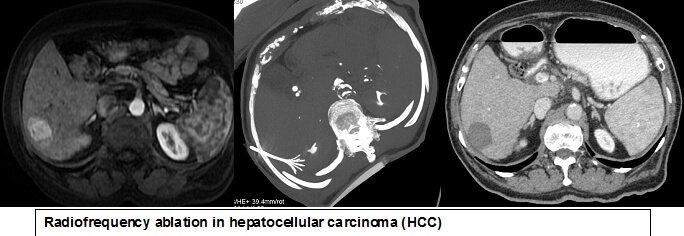
A probe is guided into the tumor and radiofrequency energy destroys it with heat.
Similar approach using microwave energy, often producing a larger, more uniform zone.
Alcohol injected directly into small tumors, dehydrating and killing the cells.
TACE (transarterial chemoembolization) is a selective, localised chemotherapy injected directly into the blood vessel supplying the liver tumor. The chemotherapy agent is mixed with iodised oil or micro-beads and injected into the tumor's own circulation — concentrating the drug at the tumor while sparing the rest of the body.
After the procedure, the tumor typically shrinks or stabilises, prolonging the patient's survival.
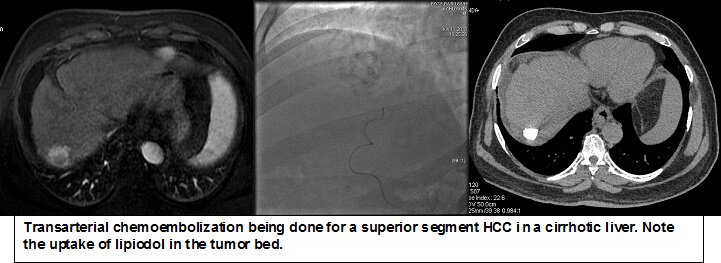
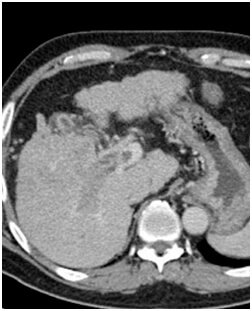
TARE is performed for patients with locally advanced liver cancer who are not suitable for liver resection or transplantation. Tumors treated include hepatocellular carcinoma (stage B and C) — including HCC with portal vein thrombosis, large inoperable HCC, borderline liver function, and multicentric HCC — plus intrahepatic cholangiocarcinoma, neuroendocrine liver metastasis, and colorectal liver metastasis.
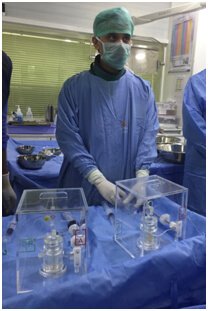
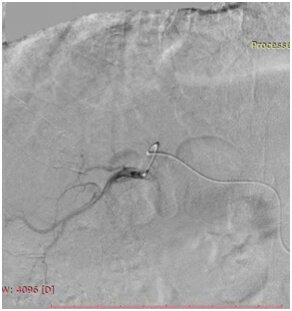
Radioactive microspheres are delivered through a catheter placed in the hepatic artery. Once infused, they lodge in vessels near the tumor and release radiation over several days — travelling only a very short distance, so effects are limited mainly to the tumor.
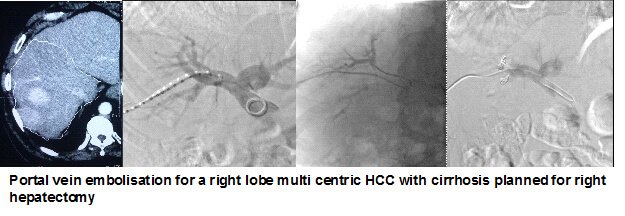
Grows the future liver remnant before surgery, increasing the number of patients eligible for curative resection.
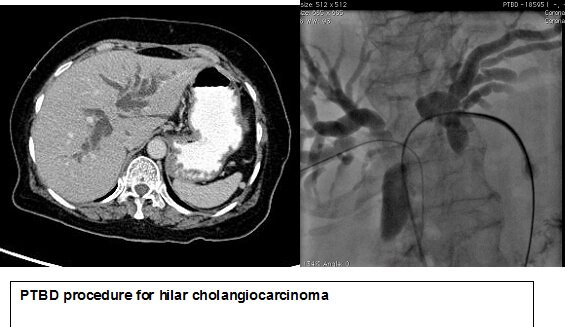
Drains blocked bile ducts caused by cancers of the liver, bile duct, pancreas, or nearby lymph nodes.
Keeps the bile duct open long-term, allowing bile to flow freely again.
Yes. Liver tumors that are inoperable or carry a high surgical risk can often be treated with minimally invasive, image-guided techniques including radiofrequency ablation, microwave ablation, TACE, and TARE, performed through a needle or catheter rather than an open operation.
Both destroy a liver tumor with heat delivered through a needle-like probe. Microwave ablation heats tissue faster and can create a larger, more uniform ablation zone, so it is often preferred for slightly larger tumors. The choice depends on the tumor's size and location.
TACE delivers chemotherapy directly into the artery feeding the liver tumor, mixed with iodised oil or micro-beads. This concentrates the drug in the tumor while sparing the rest of the body from side effects. The tumor usually shrinks or stabilises afterwards.
TARE delivers tiny radioactive microspheres through a catheter into the artery supplying the tumor, giving targeted internal radiation. It is a palliative, not curative, treatment, but it extends life, improves quality of life, and can bridge some patients to liver transplant.
TARE is used for hepatocellular carcinoma (stage B and C), including HCC with portal vein thrombosis, large inoperable HCC, borderline liver function, and multicentric HCC, as well as intrahepatic cholangiocarcinoma and neuroendocrine or colorectal liver metastases.
Portal vein embolization (PVE) can be performed first to grow the future liver remnant, making curative surgery possible for patients who would otherwise be inoperable.
PTBD (percutaneous transhepatic biliary drainage) relieves jaundice by draining the bile ducts under X-ray guidance. A stent may be placed to hold the blocked duct open.
At Neuro & Vascular, liver cancer is treated by Dr. Suresh Giragani, Consultant Interventional Radiologist at Apollo Hospitals, Jubilee Hills, Hyderabad, with over 18 years of experience including RFA, microwave ablation, TACE, and TARE.
Book a consultation with Dr. Giragani, or send your scans and reports for a specialist second opinion.